
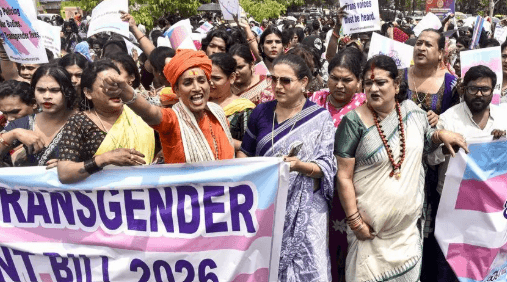
Transgender rights, healthcare should not be compromised
Context: Public health and human rights advocates have criticised the Transgender Persons Amendment Act, 2026, for replacing self-identification with mandatory medical evaluations and District Magistrate certification.

About Transgender rights, healthcare should not be compromised
What It Is?
- A parliamentary amendment to the Transgender Persons (Protection of Rights) Act, 2019, that overhauls the legal framework for gender recognition in India by replacing self-perceived gender identity with mandatory medical board evaluation and District Magistrate certification, while narrowing the statutory definition of transgender to specific biological variations and select socio-cultural identities.
Key Shifts in the Transgender Persons Amendment Act, 2026:
- Elimination of Self-Identification: Shifts the legal foundation of transgender recognition from personal autonomy and self-perceived gender identity (established under the 2019 Act and the 2014 NALSA ruling) to external medical and administrative gatekeeping.
- Mandatory Medical Board & DM Certification: Requires applicants to undergo evaluation and obtain a recommendation from a medical board, select from prescribed categories, and secure certification from a District Magistrate.
- Narrowed Statutory Definition: Removes broad, globally recognized categories such as trans men, trans women, and genderqueer persons, restricting recognition to specific variations in sex characteristics and select socio-cultural identities.
- Absence of Appellate Mechanisms: Lacks an independent review or statutory appeal process against medical board rejections or administrative delays, despite certification governing access to welfare, education, and employment entitlements.
Constitutional, Medical & Public Health Implications:
- Friction with Constitutional Jurisprudence & Global Standards:
- Contradicts the Supreme Court’s NALSA v. Union of India (2014) ruling, which affirmed gender identity as an integral part of personal dignity and autonomy under Article 21 without requiring medical intervention.
- Diverges from WHO ICD-11 guidelines and the World Professional Association for Transgender Health (WPATH) Standards of Care Version 8, reviving a discredited psychiatric and paternalistic certification model.
- Clashes with the National Human Rights Commission (NHRC) 2026 Advisory, which recommended upholding self-identification, independent grievance mechanisms, and reduced documentation barriers.
- Public Health & Clinical Consequences:
- Retreat to Unregulated Grey Markets: Ambiguity surrounding the legality of gender-affirming care has led clinicians to delay or withdraw services, pushing individuals toward unqualified providers, self-medication with hormones, and unsafe surgeries.
- Mental Health Distress: Helplines and community consultations report rising anxiety, depression, sleep disturbances, and suicidal ideation triggered by bureaucratic hurdles and exclusion.
- Exclusion from Routine Mainstream Healthcare: Beyond specialized gender-affirming clinics, transgender individuals face stigma, privacy breaches, and inadequate clinical literacy when seeking routine care for conditions like diabetes, hypertension, dental issues, or emergencies.
Existing Legal & Institutional Gaps in Healthcare:
- Unimplemented Medical Curriculum Reforms: Despite the Madras High Court’s Sushma (2021) verdict mandating LGBTQIA+ sensitivity and clinical training, revised National Medical Commission (NMC) curricula have yet to systematically integrate transgender health education.
- Non-Compliance with Grievance Redressal Mandates: Most public and private hospitals have failed to designate a statutory Complaints Officer as mandated under the 2019 Act.
- Inflexible Hospital Record Systems: Standardized admission forms and electronic health records rarely permit recording a patient’s preferred name and gender identity alongside clinically relevant anatomical data.
Way Ahead:
- Restore Self-Identification & Appellate Safeguards: Delink legal gender recognition from invasive medical board assessments, restore inclusive statutory definitions, and institute an accessible, independent appeal mechanism.
- Mainstream Transgender Clinical Training: Mandate comprehensive modules on transgender healthcare, respectful communication, and gender-affirming protocols across undergraduate medical, nursing, and hospital administration curricula via the NMC.
- Enforce Hospital Accountability & Inclusive Infrastructure: Strictly audit hospitals to ensure appointment of Complaints Officers, deploy inclusive medical record forms, and provide gender-neutral washrooms and wards.
- Guarantee Uninterrupted Gender-Affirming Care: Issue clear clinical guidelines protecting healthcare providers offering evidence-based hormone therapy and surgeries, preventing patients from being driven into unsafe, unregulated markets.
Conclusion:
Replacing self-identification with medical and administrative gatekeeping under the 2026 Amendment undermines both constitutional autonomy and public health outcomes for transgender citizens. Legal recognition and welfare eligibility must not come at the cost of bodily dignity or safe access to healthcare. Aligning domestic law with the NALSA principles, global medical standards, and inclusive hospital reforms is essential to preventing marginalization and ensuring equitable care for all.
Outline the key features of the Transgender Persons (Protection of Rights) Amendment Bill, 2026. Assess its implications for constitutional morality and fundamental rights. What measures are required to ensure a more rights-based framework?



